Being triggered is not a character flaw. It is a neurological event — one that science understands in considerable detail, and that recovery can learn to work with.
One of the most common and most damaging experiences in early recovery is what happens when a person encounters a trigger — a person, place, smell, sound, or emotional state that is associated with past substance use — and finds themselves flooded with craving, sometimes without any conscious awareness of what initiated it. The shame that follows is frequently worse than the craving itself.
The clinical term for this phenomenon is cue-induced craving, and it is one of the most extensively researched areas in addiction neuroscience. Understanding what is actually happening in the brain during these moments does not eliminate the experience. But it changes its meaning entirely.
The Neuroscience of Cue Reactivity
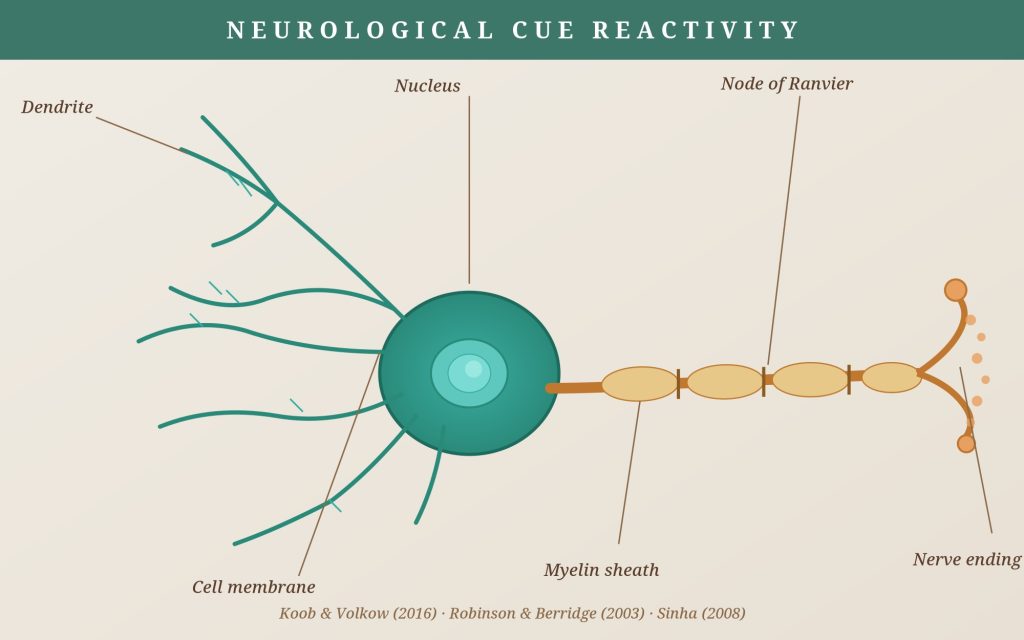
Koob and Volkow (2016) describe addiction as a disorder characterised by three recurring stages: binge and intoxication, withdrawal and negative affect, and preoccupation and anticipation. The third stage — preoccupation and anticipation — is where cue reactivity operates most powerfully. During prolonged substance use, the brain’s reward circuitry undergoes significant adaptation. The dopaminergic pathways that govern motivation, anticipation, and salience attribution become disproportionately sensitised to substance-related cues.
What this means practically is that stimuli which have been repeatedly paired with substance use — a particular neighbourhood, a certain social situation, a specific emotional state — acquire the capacity to trigger anticipatory dopamine release in the nucleus accumbens, producing a craving response that can feel, neurologically, almost identical to the original reward experience. The brain is not being irrational. It is doing exactly what it was conditioned to do.
“Cue reactivity is not a sign of weakness or lack of commitment. It is the brain executing a well-learned programme — one that took years to write and requires deliberate effort to rewrite.”
Why Shame Makes It Worse
The shame response that frequently accompanies cue-induced craving is not merely emotionally painful — it is neurologically counterproductive. Researchers have consistently demonstrated that negative affect increases craving intensity and reduces the efficacy of cognitive regulation strategies. Witkiewitz and Marlatt (2004) found that emotional dysregulation is among the strongest predictors of relapse, and shame is one of the most powerful drivers of emotional dysregulation in this population.
In short: the shame makes the craving harder to manage, not easier. It narrows the window of tolerance, reduces access to the prefrontal cortex — the region responsible for impulse control and rational decision-making — and increases the likelihood of the very behaviour it is responding to.
Working With Triggers, Not Against Them
The clinical evidence supports an approach to cue reactivity that is based on exposure, understanding, and graduated response rather than avoidance and self-condemnation. Extinction-based approaches — carefully managed exposure to triggering stimuli without the accompanying substance use — have demonstrated efficacy in reducing the intensity of cue-induced craving over time.
More immediately, psychoeducation about the neurological basis of cue reactivity has been shown to reduce shame, improve treatment engagement, and enhance the therapeutic alliance. When people understand that their brain is responding to conditioning rather than revealing something defective about their character, the quality of their engagement with recovery changes.
You were triggered because your brain learned something, over a long period of time, with considerable reinforcement. That learning can be revised. It is slow work. But it is not impossible — and it is not your fault.
References
- Koob, G. F., & Volkow, N. D. (2016). Neurobiology of addiction: A neurocircuitry analysis. The Lancet Psychiatry, 3(8), 760–773.
- Witkiewitz, K., & Marlatt, G. A. (2004). Relapse prevention for alcohol and drug problems: That was Zen, this is Tao. American Psychologist, 59(4), 224–235.
- Robinson, T. E., & Berridge, K. C. (2003). Addiction. Annual Review of Psychology, 54(1), 25–53.
- Sinha, R. (2008). Chronic stress, drug use, and vulnerability to addiction. Annals of the New York Academy of Sciences, 1141(1), 105–130.
Understanding your triggers is the first step. Building a personalised response plan is the next. Relapse prevention planning is available through Healing Light SA.